Quick Answer: The most common cause of arthritis in the back is osteoarthritis of the facet joints, driven by cartilage change, aging, altered spinal load, and prior injury. Inflammatory diseases such as axial spondyloarthritis, psoriatic arthritis, or rheumatoid arthritis can also affect the spine. Infection and crystal disease are less common but important alternatives.
Spinal arthritis is not one condition. It can involve the small facet joints, sacroiliac joints, ligaments, or other spinal structures. Separating degenerative wear from inflammatory disease matters because the symptom pattern, tests, and treatment can be very different.
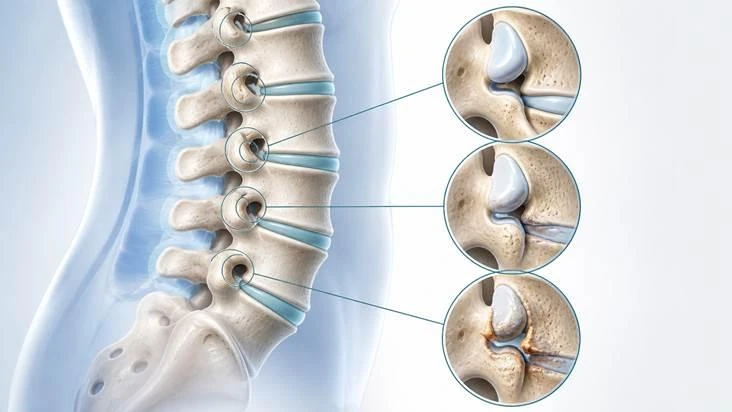
Types of Arthritis in the Back
| Type | Typical mechanism | Common clues |
|---|---|---|
| Facet osteoarthritis | Cartilage and joint change over time | Activity-related pain, stiffness, limited motion |
| Axial spondyloarthritis | Immune-driven inflammation | Morning stiffness, night pain, improvement with movement |
| Psoriatic or enteropathic arthritis | Inflammation linked to psoriasis or bowel disease | Back symptoms plus skin, nail, or intestinal features |
| Rheumatoid arthritis | Autoimmune synovial inflammation | More often affects the upper cervical spine |
| Infectious or crystal arthritis | Infection or crystal deposition | Acute severe pain, fever, or systemic illness may occur |
The Most Common Cause: Facet-Joint Osteoarthritis
Facet joints guide motion at the back of each spinal segment. Their cartilage can thin and the underlying bone can remodel, producing joint-space narrowing, sclerosis, cysts, or osteophytes. Disc height loss may shift more load to the facets, so degenerative disc and joint changes often occur together.
SpineDocs provides related explanations of degenerative disc disease and spinal arthritis management. Imaging findings are common with age and do not prove that a particular joint is painful.
Key Takeaway: Facet osteoarthritis develops through interacting cartilage, bone, disc, and load changes, not simple wear alone.
Risk Factors for Degenerative Arthritis in the Back
Aging increases the likelihood of structural change, but risk is also shaped by genetics, previous fractures or joint injury, repetitive heavy loading, smoking, reduced conditioning, and conditions that alter spinal alignment. Excess body weight may increase mechanical and metabolic stress, although it should not be treated as a moral failing or a single cause.
Posture can change symptoms and short-term loading, but evidence does not support blaming one everyday posture as the sole cause of spinal arthritis. A more accurate model considers lifetime exposure, recovery capacity, muscle function, injury history, and inherited biology.
Key Takeaway: Risk is multifactorial, so no single habit or posture explains most cases of degenerative spinal arthritis.
Inflammatory Causes of Arthritis in the Back
Axial spondyloarthritis can inflame the sacroiliac joints and spine, often beginning before age 45. Clues include morning stiffness lasting well beyond a few minutes, waking in the second half of the night, alternating buttock pain, improvement with activity, psoriasis, inflammatory bowel disease, uveitis, or a family history.
Psoriatic, reactive, and enteropathic arthritis can also involve the spine. Rheumatoid arthritis more commonly affects the upper cervical region than the low back. Blood tests can support a suspected inflammatory diagnosis, but no single test confirms every case. Early rheumatology involvement may prevent delays.
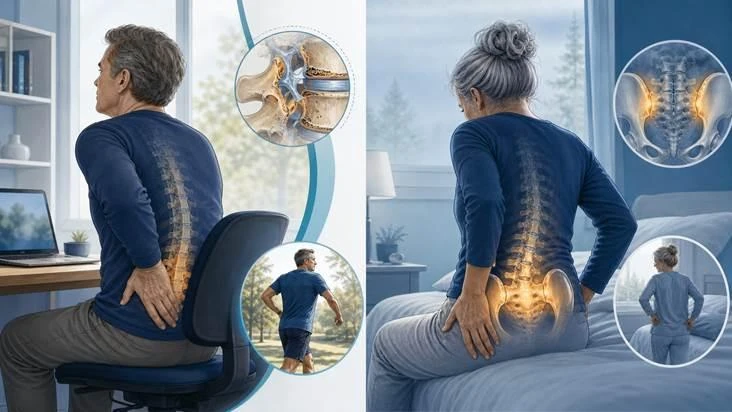
Key Takeaway: Back pain that improves with activity and comes with prolonged morning stiffness or systemic features deserves inflammatory evaluation.
Less Common Causes and Complications
Joint infection can cause severe localized pain with fever or illness, especially after bloodstream infection, surgery, injection, or in people with immune suppression. Crystal deposition, including calcium pyrophosphate disease, can occasionally involve spinal joints and ligaments. These conditions need targeted testing because routine osteoarthritis care is not enough.
Degenerative enlargement and bone spurs can narrow the canal or nerve exits, contributing to spinal stenosis, leg pain, numbness, or weakness. Arthritis may be part of the narrowing without being the only pain generator.
Key Takeaway: Acute systemic illness or neurologic symptoms should not be assumed to be routine arthritis.
Symptoms and Diagnosis
Mechanical spinal arthritis often causes localized aching, stiffness after rest, reduced motion, and pain with extension or rotation. Inflammation can produce longer morning stiffness and night pain. Nerve compression may add radiating pain, tingling, numbness, or weakness. Symptoms alone cannot identify the exact joint.
A SpineDocs diagnostic evaluation may include a neurologic and musculoskeletal examination. X-rays show alignment and bony change, while MRI better displays nerves, discs, marrow, and active inflammation. Laboratory tests are used selectively when infection or inflammatory arthritis is possible.
Key Takeaway: Imaging can confirm structural change, but diagnosis still depends on whether findings match the clinical pattern.
Treatment Depends on the Cause
Degenerative arthritis care commonly combines education, graded aerobic activity, strengthening, mobility work, sleep support, and medication when safe. Weight management may reduce load for some patients. Injections can provide diagnostic information or temporary relief in selected cases, while surgery is reserved for specific structural problems or neurologic compromise.
Inflammatory arthritis may require disease-modifying treatment from a rheumatologist. SpineDocs' pain-management overview explains why treatment should match the identified pain source rather than an imaging label alone.

Key Takeaway: The right treatment targets the arthritis type, current function, and any nerve involvement.
Best Practices
- Describe when stiffness occurs, how long it lasts, and what improves it.
- Report psoriasis, eye inflammation, bowel disease, fever, or family history.
- Build activity gradually and include both aerobic and strengthening work.
- Review medication risks with a clinician, especially with kidney, stomach, heart, or bleeding concerns.
Key Takeaway: A detailed symptom pattern and steady activity plan make care more precise and sustainable.
Common Mistakes
- Assuming every imaging change is the source of pain.
- Blaming poor posture as the only cause.
- Using prolonged rest, which can reduce strength and tolerance.
- Missing inflammatory clues because the pain is called ordinary arthritis.
- Using supplements or medicines without checking interactions and evidence.
Key Takeaway: Overinterpreting scans and overlooking inflammatory features are two avoidable sources of delayed care.
Conclusion
The causes of arthritis in the back range from common facet-joint osteoarthritis to immune-driven disease and uncommon infection or crystal deposition. Age and injury contribute, but imaging changes are not a complete explanation for pain. A careful pattern-based evaluation leads to safer, more specific treatment.
Key Takeaway: Identifying degenerative, inflammatory, or uncommon causes is the first step toward appropriate care.
Resources and References
- Johns Hopkins Medicine: Spinal Arthritis
- NIAMS: Osteoarthritis
- American College of Rheumatology: Axial Spondyloarthritis
- Southeast Texas Spine: What Is Causing My Spinal Arthritis?
- ADR Spine: Arthritis of the Spine Symptoms
Key Takeaway: These sources support the degenerative, inflammatory, diagnostic, and management concepts summarized here.
Request an Appointment
Ready to discuss your symptoms or treatment options? Request an appointment with SpineDocs | Montesano Spine & Sport for an individualized evaluation.
SpineDocs | Montesano Spine & Sport
Phone: (941) 402-4003